
- Hypermobile hip exercises we use, and why clamshells aren’t one of them - 17 October 2026
- Is Fibromyalgia a Disability in the UK, and Can You Claim PIP? - 14 October 2026
- Fibromyalgia and Central Sensitisation, What Is It in Plain English? - 8 October 2026
This article is part of our comprehensive guide to exercise and rehabilitation for hypermobility.
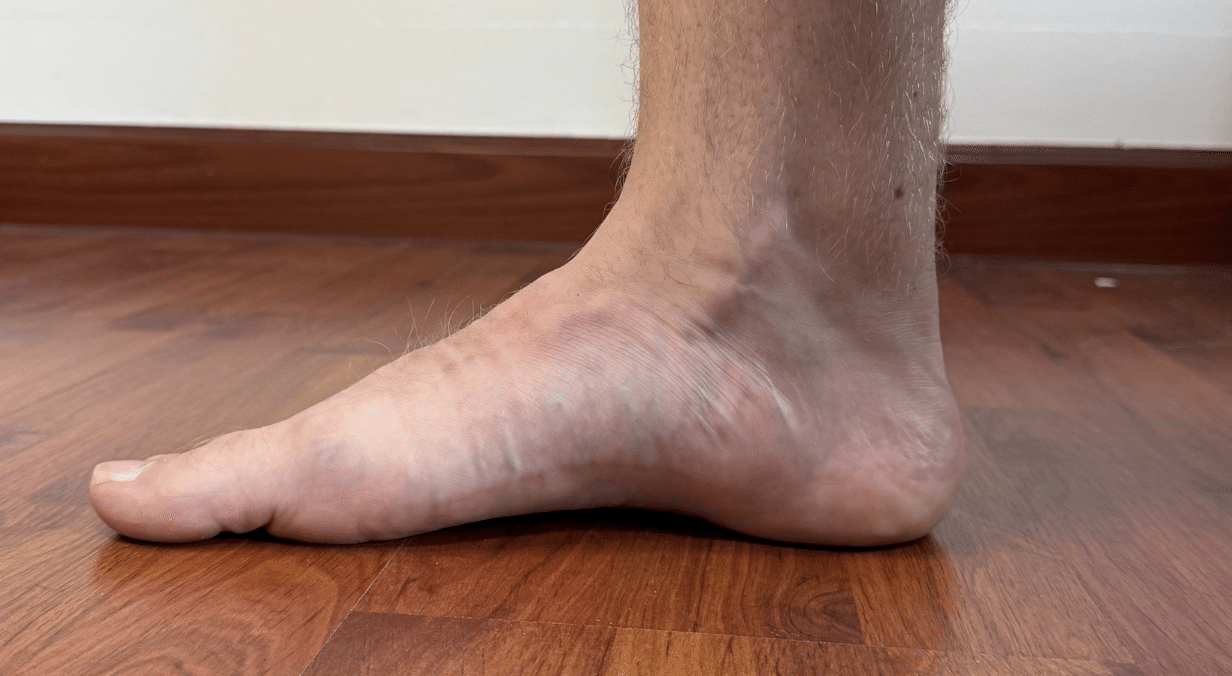
Most of those with hypermobility who go looking for foot arch exercises have already been told the same two things, that your arches have collapsed and that you need to strengthen your feet, usually with a pair of insoles handed over at the same time. That advice isn’t mad, it’s just aimed at the wrong thing, as your arch isn’t a structure that’s given up under the weight of you. It’s a shape your foot is meant to make and unmake a few thousand times a day, and in hypermobile feet it’s the making and unmaking that goes wrong, rather than the shape somebody sees while you’re stood still on a plinth.
So this is what the arch actually does, why yours stops doing it, and the two exercises we use with clients more than anything else.
What your arch is actually doing
Your arch isn’t a fixed shape, it’s a moves, or at least it’s supposes to. Every step it drops, stores a bit of energy in the tissue underneath, then rises again to give you something stiff to push off from. Flatten and rebuild, flatten and rebuild, all the way to the kitchen and back, without you ever giving it a thought.
For that to work, your brain needs to know where your foot is and what the floor is doing, moment to moment. The sole is very well set up for the job, with four classes of receptor sitting in the skin there, feeding into balance both consciously and through much faster reflex routes you never become aware of [1]. Model what happens during actual walking rather than standing about, and the toes, the heel and the outer border seem to do a particularly large amount of the reporting [2].
Now, the difference in a hypermobile foot isn’t the receptors, it’s the tissue they’re sitting in. More compliant tissue deforms further for the same load, and it takes longer to pull tight enough to set those receptors off. The information still arrives, it just arrives a bit late and a bit vague about how much. A brain making movement decisions on a vaguer signal, makes vaguer decisions, and what you feel at the end of all that is an arch that gives way at a moment you weren’t expecting it to.
Which is why this is an information problem before it’s a strength problem.
Why the shape of your foot matters less than you’d think
Standing still while somebody looks at your arch height measures your foot at rest, and rest isn’t where your difficulty lives. The best look anybody has had at hypermobile feet while they were actually walking, in adults with hEDS and HSD, found no arch category at all. What it found was the smaller segments of the foot moving more than they should, particularly through the inside of the forefoot [3]. Small group, exploratory, so hold it loosely, but it’s the most relevant thing there is.
Whether hypermobile feet are flatter as a rule hasn’t been settled either. Hypermobility tracks with a more pronated foot posture in some groups of young adults [4], and makes no difference at all in others [5], and a good chunk of that work was done in children, which is a real limitation if you’re thirty four and reading this.
The useful question isn’t what shape your foot is. It’s what your foot does when you put your weight through it.
The three points of contact
A foot that’s standing well has three points on the floor: the base of the big toe, the base of the little toe, and the middle of the heel. Think of a tripod, as lose one leg of a tripod and the whole thing tips over, and that’s more or less what happens in a foot.
The pattern we see most is the base of the big toe quietly stopping taking any load. Weight drifts to the inside of the heel and the inner midfoot, the arch flattens as a consequence of that rather than as the cause of it, and the big toe ends up a passenger. The less common version is the whole foot loading onto its outer border instead, which is the same problem in a different coat, two points doing the work of three.
Have a go now. Stand up, bare feet, and push gently into all three points at the same time, without clenching your toes or curling them under. Most people feel one of the three go missing inside about ten seconds, and finding out which one you lose is the whole exercise at this stage.
The tripod is a teaching tool rather than a finding, by the way, and nobody has run a trial on cueing it. We use it because it’s something you can actually feel and act on, which matters a great deal more than it sounds when the underlying problem is information.

Your shin does more for your arch than your foot does
This is the part that surprises people. Turn your shin bone inwards and your arch lowers. Turn it outwards and your arch rises. You don’t have to do anything at the foot at all, as the joint underneath your ankle behaves more like a screw thread than a hinge, so rotation up the leg and movement at the heel are mechanically tied to one another [6].
Which is why squeezing away at the foot on its own tends to disappoint. If the shin and the hip above it never rotate, the foot has nothing to respond to, and you’ve spent eight weeks training a small muscle to produce force in a foot whose actual difficulty was timing.
The arch control pattern
Theory only takes you so far with this one, you need to see it. The video below is the arch control and loading pattern we teach, and it’s the base that everything else sits on.
A few things worth knowing before you copy it.
– All three points stay down: the commonest error is pushing into the inside of the heel and letting the base of the little toe lift, or pushing to the outside and letting the big toe lift. A point coming off the floor means you’ve gone past your range, so it’s a cue to come back, not to push harder.
– Toes stay long: gripping with the toes is the single most common substitution we see. It’s the toe flexors doing a job that belongs further up the leg, and it’s why people’s soles cramp after a week of arch exercises.
– Go slowly: fast reps get done on momentum, and momentum doesn’t need the information you’re trying to train. Speed hides need, every time.
– The lean is the point: you aren’t holding a static arch here. You’re holding the shape while the direction of the load moves underneath it, which is what gives the foot something to report on.
Adding the knee
Once that pattern’s dialled in, this is our favourite progression, and it ties the last two sections together.
The knee travels, which rotates the shin, which asks the arch to lift and drop, and your job is to keep all three points on the floor while it happens. Same rules as before, toes long, slowly, and stop when a point lifts rather than fighting to hold the position. Five or ten good rebuilds a side is worth considerably more than forty minutes of an arch propped up by hope.
Why just strengthening the foot usually isn’t enough
The short foot exercise (drawing the ball of your foot towards your heel without curling the toes) is the standard prescription, and it does do something. Pooled work on training the small muscles inside the foot shows improvements in arch drop, foot posture scores, balance and strength, with no advantage at all for reducing pain [7].
That’s worth reading twice. It moves the numbers on a ruler more reliably than it moves how somebody feels.
And not one of those trials was done in a hypermobile population. Not one. Every short foot recommendation you’ll read, ours included, is an extrapolation from people with flexible flat feet who don’t have a connective tissue difference underneath it. We think it’s a reasonable extrapolation, and you should still know that’s what it is.
Orthotics
Orthotics get treated as either the cure or the enemy, and they’re neither.
What they definitely do is change what your foot does while you’ve got them on. Custom devices, hard or soft, measurably raise the arch during walking, and the versions off the shelf do rather less of it [8]. They move pressure about, usually off the heel and forefoot and into the midfoot, and in several conditions they bring pain down.
What they don’t do is rebuild your arch. Nothing in the pooled adult flat foot work reliably changes arch drop, and that includes the exercises [9].
We used to say that orthotics weaken your feet over time. That was too strong, and we’ve taken it out. Twelve weeks in custom orthoses did shrink three of the small foot muscles in young adults with flat feet [10], but nine weeks of arch support in young footballers made two of those muscles bigger [11], and three months of prefabricated devices in healthy adults changed nothing about the tissue at all [12]. Shrank in one group, grew in another, unchanged in a third. Age, foot type, device design and whether anybody was also doing some exercise all look like they matter a great deal more than the orthotic on its own.
The genuinely useful finding is that insoles plus foot work beat insoles alone for pain and function in symptomatic flexible flat feet, while arch drop came down about the same either way [13].
For hypermobility in particular, there’s nothing randomised at all on orthoses, splints, taping or footwear in children with HSD or hEDS [14], and we couldn’t find anything in adults either. So if an insole lets you walk further with less pain, keep it and train alongside it. Wearing one forever and never working the foot has no evidence behind it in either direction, and we know which way we’d bet.
How long this takes, and what usually goes wrong
Nothing here works in a fortnight.
The sensory side moves reasonably quickly, in a few weeks, as in feeling where your foot actually is, noticing a point lifting, catching a collapse before it’s finished happening. Control under load takes longer, and a couple of months of consistent work before walking feels different is normal. Shape change, if it comes at all, is a long way further out, and since none of the treatments in the literature reliably shift arch drop anyway [9], don’t make shape the target.
The sensory side does look trainable in hypermobile people, though the direct evidence is thin. Two weeks of plantar sensory stimulation in asymptomatic young adults with generalised hypermobility improved how accurately they could place a joint, against a control group who got a leaflet [15]. Asymptomatic, young, two weeks, small. It’s one piece of work and it’s the only direct evidence there is, so it’s encouraging rather than settled.
The mistakes we see, in rough order of how often they turn up:
– Gripping with the toes: it feels productive, it trains the wrong muscles, and it’s why your foot cramps by Thursday.
– Going for length instead of quality: five good rebuilds beats forty minutes of a collapsed arch held in place by willpower.
– Training the foot and nothing above it: if the shin and the hip never rotate, the foot has nothing to respond to.
– Stopping the moment it stops hurting: this is the one that puts people back at the start six months later.
Start with the three points. Then the pattern in the first video, slowly, until you can hold it without gripping. Then add the knee.
The Fibro Guy

References
[1] Strzalkowski, N.D.J., Peters, R.M., Inglis, J.T. and Bent, L.R. (2018) ‘Cutaneous afferent innervation of the human foot sole: what can we learn from single-unit recordings?’, Journal of Neurophysiology. https://doi.org/10.1152/jn.00848.2017
[2] Katic, N., Siqueira, R.K., Cleland, L., Strzalkowski, N., Bent, L., Raspopovic, S. et al. (2023) ‘Modeling foot sole cutaneous afferents: FootSim’, iScience. https://doi.org/10.1016/j.isci.2022.105874
[3] Vermeulen, S., De Mits, S., De Ridder, R., Calders, P., De Schepper, J., Malfait, F. et al. (2022) ‘Altered Multisegment Ankle and Foot Kinematics During Gait in Patients With Hypermobile Ehlers‐Danlos Syndrome/Hypermobility Spectrum Disorder: A Case–Control Study’, Arthritis Care & Research. https://doi.org/10.1002/acr.24526
Read More[4] Alahmari, K.A., Kakaraparthi, V.N., Reddy, R.S., Samuel, P.S., Tedla, J.S., Rengaramanujam, K. et al. (2021) ‘Foot Posture Index Reference Values among Young Adults in Saudi Arabia and Their Association with Anthropometric Determinants, Balance, Functional Mobility, and Hypermobility’, BioMed Research International. https://doi.org/10.1155/2021/8844356
[5] Martinez-Sebastian, C., De La Fuente, M.C.C., Gijon-Nogueron, G., Gomez-Carrion, A., Ramos-Petersen, L. and Evans, A.M.F. (2026) ‘Ankle muscle strength, joint hypermobility, and foot posture in children aged 5–10 years: A cross-sectional study’, European Journal of Pediatrics. https://doi.org/10.1007/s00431-026-07313-7
[6] Fischer, K.M., Willwacher, S., Arndt, A. and Brüggemann, G. (2018) ‘Calcaneal adduction and eversion are coupled to talus and tibial rotation’, Journal of Anatomy. https://doi.org/10.1111/joa.12813
[7] Jaffri, A.H., Koldenhoven, R., Saliba, S. and Hertel, J. (2023) ‘Evidence for Intrinsic Foot Muscle Training in Improving Foot Function: A Systematic Review and Meta-Analysis’, Journal of Athletic Training. https://doi.org/10.4085/1062-6050-0162.22
[8] Balsdon, M., Dombroski, C., Bushey, K. and Jenkyn, T.R. (2019) ‘Hard, soft and off-the-shelf foot orthoses and their effect on the angle of the medial longitudinal arch’, Prosthetics & Orthotics International. https://doi.org/10.1177/0309364619825607
[9] Hoang, N.T.T., Chen, S. and Chou, L.W. (2021) ‘The Impact of Foot Orthoses and Exercises on Pain and Navicular Drop for Adult Flatfoot: A Network Meta-Analysis’, International Journal of Environmental Research and Public Health. https://doi.org/10.3390/ijerph18158063
[10] Protopapas, K. and Perry, S.D. (2020) ‘The effect of a 12-week custom foot orthotic intervention on muscle size and muscle activity of the intrinsic foot muscle of young adults during gait termination’, Clinical Biomechanics. https://doi.org/10.1016/j.clinbiomech.2020.105063
[11] Hikawa, K., Tsutsui, T., Ueyama, T., Yang, J., Hara, Y. and Torii, S. (2022) ‘Effects of a 9-weeks arch support intervention on foot morphology in young soccer players: a crossover study’, BMC Sports Science, Medicine and Rehabilitation. https://doi.org/10.1186/s13102-022-00590-3
[12] Reeves, J., Jones, R., Liu, A., Bent, L., Martinez-Santos, A. and Nester, C. (2021) ‘No change in foot soft tissue morphology and skin sensitivity after three months of using foot orthoses that alter plantar pressure’, Footwear Science. https://doi.org/10.1080/19424280.2021.1961880
[13] ELSAYED, W., ALOTAIBI, S., SHAHEEN, A., FAROUK, M. and FARRAG, A. (2023) ‘The combined effect of short foot exercises and orthosis in symptomatic flexible flatfoot: a randomized controlled trial’, European Journal of Physical and Rehabilitation Medicine. https://doi.org/10.23736/s1973-9087.23.07846-2
[14] Peterson, B., Coda, A., Pacey, V. and Hawke, F. (2018) ‘Physical and mechanical therapies for lower limb symptoms in children with Hypermobility Spectrum Disorder and Hypermobile Ehlers‐Danlos Syndrome: a systematic review’, Journal of Foot and Ankle Research. https://doi.org/10.1186/s13047-018-0302-1
[15] Yildiz, R., Yildiz, A., Camli, O., Akkaya, H., Aydin, M. and Basaran, Z. (2025) ‘Effect of Plantar Sensory Stimulation on Sensorimotor Organization in General Joint Hypermobility: A Randomized Controlled Study’, Healthcare. https://doi.org/10.3390/healthcare13202572