

- Swollen legs and hypermobility: pooling, lymphoedema and lipoedema - 4 November 2026
- Walking with fibromyalgia - 2 November 2026
- Water exercise and hydrotherapy for fibromyalgia - 2 November 2026
This article is part of our comprehensive guide to POTS and dysautonomia.
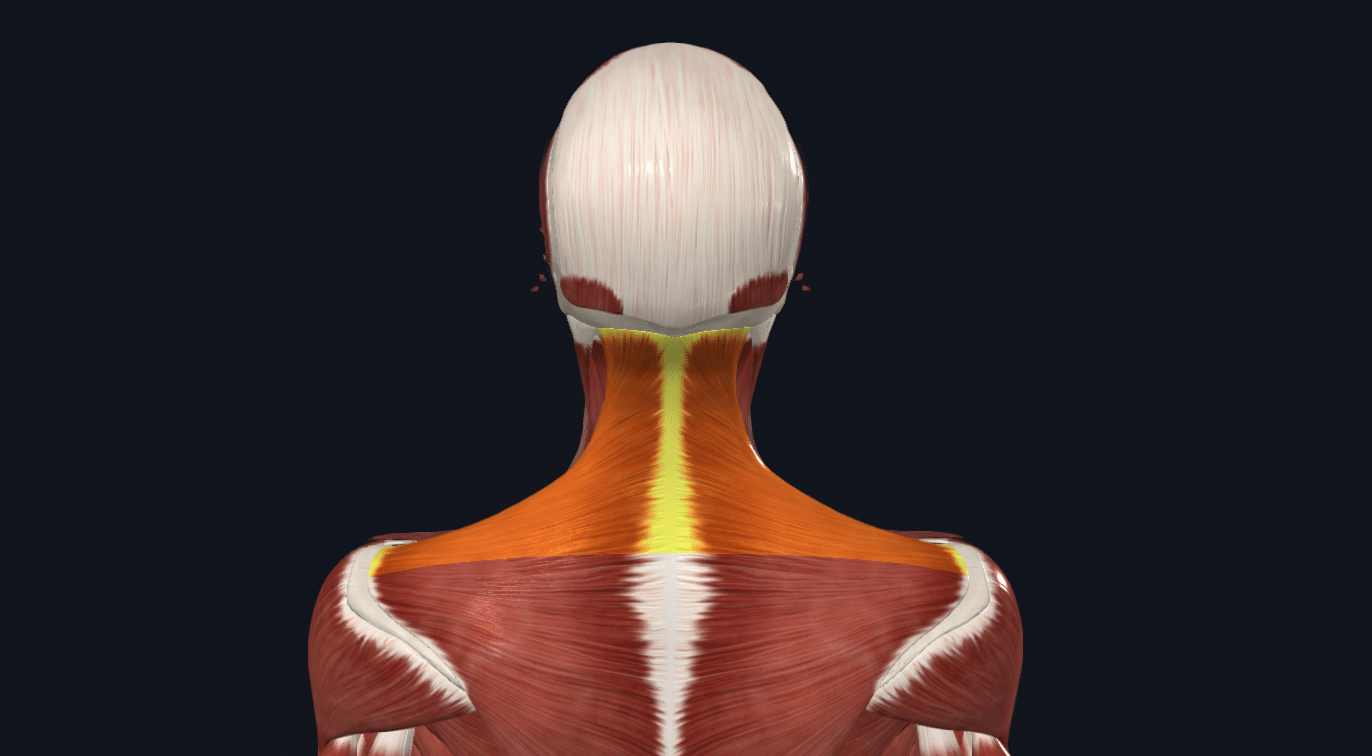
A dull, dragging ache across the back of your neck and over the tops of your shoulders, one that gets worse the longer you’re upright and eases off once you lie down, actually has a name. Draw the shape of it on a body, base of the skull, either side of the neck, out across the shoulders, and you’ve got the rough outline of a coat hanger, which is where the name came from [1].
Most people who get it have been told it’s their posture, or that they carry their stress in their shoulders, and have been sent off with a stretch for it. Which is a bit of a shame really, as what seems to drive it has very little to do with either.
What makes it coat hanger pain
Plenty of things will make a neck and a pair of shoulders ache, so what marks this one out isn’t really where it sits, it’s what it tracks. Coat hanger pain turns up when you’re upright, it builds the longer you stay there, and it settles once you lie flat [1]. If yours does that, it’s a clue worth following rather than something to file under bad posture and forget about.
It has been measured most carefully in people with autonomic failure, which is where the automatic side of the nervous system has stopped doing the blood pressure job properly, so the drop on standing is large and easy to record [1].
Why it lands in the neck and shoulders
The muscles holding your head up are working the entire time you’re vertical, so if your blood pressure drops when you stand, those muscles get rather less than they’re asking for. The same coupling, between this neck pain and the size of the blood pressure drop on sitting up, turns up in spinal cord injury too, which is a completely different route to the same problem [2]. And when the trapezius itself is measured during a tilt in people with autonomic failure who get this ache, it behaves the way a muscle behaves when it’s running short of blood [3]. None of which is hand waving, as there’s something genuinely measured underneath it.
It isn’t the whole story though. If this were purely a blood pressure problem then strapping somebody to a table and tipping them upright would reproduce the pain every time, and it doesn’t. Far more people describe the ache in ordinary life than ever produce it on the table [4]. Something else is loading it as well: how long you’ve been up, how hard those muscles are working, heat, food, and how your nervous system is handling the signal coming back from a muscle that’s struggling.

If you have POTS or hypermobility
POTS is defined by the heart rate climbing on standing without the blood pressure falling [5], so the mechanism above, which was measured in people whose blood pressure does fall, isn’t automatically yours. The two groups overlap heavily, mind. When one sample of people carrying a POTS diagnosis was assessed properly, around a third of them met the criteria for hEDS and a good many more were hypermobile without quite meeting them [6]. Those were people who’d turned up to a dysautonomia conference in the first place though, so take it as an overlap worth knowing about rather than a population rate.
What we can’t hand you is a paper counting this particular ache in POTS or in hypermobility. What we do have is a great many people in front of us in the studios with an ache in exactly that distribution, behaving in exactly that way, and in our opinion that’s reason enough to go and look at the orthostatic side of things. It’s nowhere near enough to call it a diagnosis.
What helps
The dull things come first, unfortunately: a proper look at anything you’re already taking that lowers your blood pressure, getting fluid and volume up, compression over the abdomen rather than the legs alone, and counter manoeuvres like crossing your legs or having a squat when you feel it building [7][8]. Lying down will reliably end an episode, which is handy on the day and not much of a plan for the year.
Two of those get handed out constantly and argued about endlessly, and both are worth reading properly rather than taking on trust. What the evidence supports for compression garments is a good deal more specific than “wear something tight”, and the salt advice everybody gets given is considerably shakier than the confidence it arrives with.
Now, the harder one. Doing less of being upright is exactly what makes being upright harder, and graded exercise that starts horizontal or semi recumbent and builds slowly has the most behind it for POTS [9]. It’s also, reliably, the thing people get offered last, if at all.
Two things worth checking
Neither of these replaces the dull stuff above, and neither of them is standard advice. They’re just the two we keep ending up at, and they’re both cheap to go and check.
Breathing, and carbon dioxide
Start with the part that isn’t ours, as a good deal of this has actually been measured. When somebody with POTS stands up the breathing tends to go up with it, and breathing harder blows off carbon dioxide, which is one of the things keeping the blood vessels in your brain open. Measured during a tilt, carbon dioxide runs lower in POTS than it does in people without it and blood flow to the brain falls a good deal further. Once you account for the carbon dioxide, the difference between the two groups isn’t there at all [10]. That last part is the bit that earns it, as it says the carbon dioxide is doing the work rather than simply sitting alongside it.
If you’ve ever wondered why the brain fog gets worse the longer you stay on your feet, that’s the same plumbing.
It has been looked at in hypermobility specifically too. Adults with hEDS who also had POTS went into a scanner while blood was drawn down into their legs, which is standing up without the standing up. Their breathing sped up and their carbon dioxide fell, neither of which happened in the people without hEDS, and pushing blood through the brain got considerably harder than it did in the controls [11]. Nobody’s blood pressure moved at all. Take it gently though, as it was a small group, every one of them had POTS as well so you can’t pull the hEDS apart from it, and the authors call that part of their own work hypothesis generating.
Not everybody is running low on it, mind. Tilt a group of people with POTS and in one small study half of them were and half of them weren’t [12], so it’s a real mechanism in a decent chunk of people rather than the explanation for everything.
So, the part that’s genuinely ours, and pinch of salt on this one please. Working on breathing, and specifically on building a bit more tolerance to carbon dioxide rather than blowing it off all day long, seems to take the edge off the coat hanger ache for a lot of our clients (which we honestly didn’t expect, and still can’t fully explain). We can’t hand you a trial for it. What makes it worth a go anyway is that the two problems share equipment. If your breathing has drifted up into your chest then your neck and the tops of your shoulders are doing a share of it all day, and those are the same muscles already being asked to hold your head up.
How we actually start that, and why breathing comes before anything upright at all, is set out in POTS and exercise.
Shoulder blades, and upward rotation
To get your arm overhead, your shoulder blade has to rotate upwards. That job belongs mostly to two muscles working as a pair: the serratus anterior, which runs along your ribs under the armpit, and the lower trapezius, which runs down between your shoulder blades, with the upper trapezius helping out indirectly [13]. Anecdotally, most of our clients with coat hanger pain can’t produce that upward rotation when you ask them for it. It isn’t so much weak as missing, and if you ask for it, what you tend to get back is a shrug.
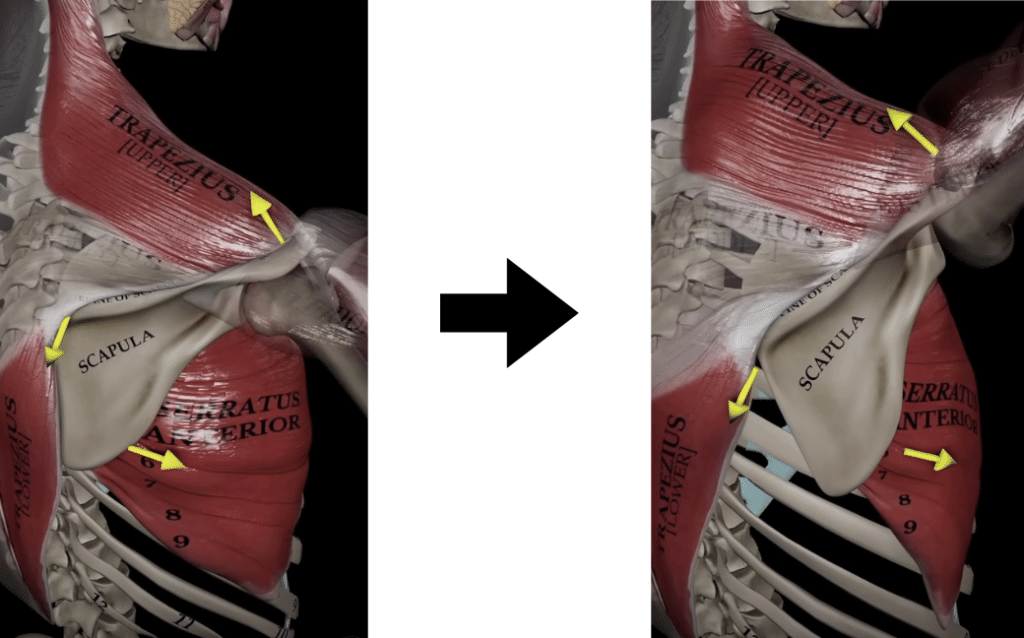
That matters for reasons that have nothing to do with blood pressure. In shoulders with impingement, less upward rotation goes with less room under the acromion (the bony shelf on the top of your shoulder) as the arm comes up, which is one of the routes to an irritated rotator cuff [14]. In those with hEDS or HSD who also have multidirectional shoulder instability, that upward rotation is reduced [15], and shoulder pain is reported by the large majority of adults with hEDS and HSD [16]. So the shoulder girdle being asked to hold your head up all day, is quite often a shoulder girdle that can’t do one of its own basic jobs either.
A shoulder blade that moves oddly turns up in plenty of people with no shoulder pain whatsoever though, so on its own it isn’t a diagnosis [17]. And in women with fibromyalgia the measured pattern points the other way entirely, towards more upward rotation rather than less [18]. We’re not telling you that missing upward rotation causes coat hanger pain, as we’ve got nothing that shows it. We’re telling you it’s a separate and extremely common problem in the same bit of the body, it’s worth having back, and hardly anybody ever gets checked for it.
A short way in to scapular upward rotation, and why overhead tasks are such a drama without it.
When to get it looked at
All of the above is for the ordinary postural version of this, once the alarming causes have been ruled out by somebody who’s actually looked at you. Go and get seen in person if any of the following fits.
– Severe pain: not the usual dragging ache, but genuinely severe.
– More headache than ache: it reads like a headache, and it’s clearly worse upright.
– Neurological symptoms: double vision, trouble swallowing, or weakness in an arm or a leg.
– Steadily getting worse: building month on month rather than settling into a pattern.
The Fibro Guy

References
[1] Bleasdale-Barr, K.M. and Mathias, C.J. (1998) ‘Neck and other muscle pains in autonomic failure: their association with orthostatic hypotension’, Journal of the Royal Society of Medicine. https://doi.org/10.1177/014107689809100704
[2] Cariga, P., Ahmed, S., Mathias, C. and Gardner, B. (2002) ‘The prevalence and association of neck (coat-hanger) pain and orthostatic (postural) hypotension in human spinal cord injury’, Spinal Cord. https://doi.org/10.1038/sj.sc.3101259
[3] Humm, A.M., Bostock, H., Troller, R. and Z’Graggen, W.J. (2011) ‘Muscle ischaemia in patients with orthostatic hypotension assessed by velocity recovery cycles’, Journal of Neurology, Neurosurgery & Psychiatry. https://doi.org/10.1136/jnnp-2011-300444
Read More[4] Khurana, R.K. (2012) ‘Coat-hanger ache in orthostatic hypotension’, Cephalalgia. https://doi.org/10.1177/0333102412449932
[5] Chung, T.H. and Raj, S.R. (2026) ‘Postural Orthostatic Tachycardia Syndrome (POTS)’, JAMA. https://doi.org/10.1001/jama.2026.14809
[6] Miller, A.J., Stiles, L.E., Sheehan, T., Bascom, R., Levy, H.P., Francomano, C.A. et al. (2020) ‘Prevalence of hypermobile Ehlers-Danlos syndrome in postural orthostatic tachycardia syndrome’, Autonomic Neuroscience. https://doi.org/10.1016/j.autneu.2020.102637
[7] Wieling, W., Kaufmann, H., Claydon, V.E., van Wijnen, V.K., Harms, M.P.M., Juraschek, S.P. et al. (2022) ‘Diagnosis and treatment of orthostatic hypotension’, The Lancet Neurology. https://doi.org/10.1016/s1474-4422(22)00169-7
[8] Moloney, D., Youssef, A. and Okamoto, L.E. (2026) ‘Management of Orthostatic Hypotension’, JAMA Internal Medicine. https://doi.org/10.1001/jamainternmed.2026.0284
[9] Fu, Q. and Levine, B.D. (2018) ‘Exercise and non-pharmacological treatment of POTS’, Autonomic Neuroscience. https://doi.org/10.1016/j.autneu.2018.07.001
[10] Novak, P. (2018) ‘Hypocapnic cerebral hypoperfusion: A biomarker of orthostatic intolerance’, PLOS ONE. https://doi.org/10.1371/journal.pone.0204419
[11] Gerlach, D.A., Bach, A., de Boni, L., Fischer, F., Barth, T., Hoff, A. et al. (2026) ‘Excessive Hypocapnic Cerebral Vasoconstriction in Hypermobile Ehlers–Danlos Syndrome Assessed With Real‐Time Magnetic Resonance Imaging During Lower‐Body Negative Pressure’, Journal of the American Heart Association. https://doi.org/10.1161/jaha.126.050302
[12] Stewart, J.M., Medow, M.S., Cherniack, N.S. and Natelson, B.H. (2006) ‘Postural hypocapnic hyperventilation is associated with enhanced peripheral vasoconstriction in postural tachycardia syndrome with normal supine blood flow’, American Journal of Physiology-Heart and Circulatory Physiology. https://doi.org/10.1152/ajpheart.01359.2005
[13] Phadke, V., Camargo, P. and Ludewig, P. (2009) ‘Scapular and rotator cuff muscle activity during arm elevation: a review of normal function and alterations with shoulder impingement’, Brazilian Journal of Physical Therapy. https://doi.org/10.1590/s1413-35552009005000012
[14] Lefèvre-Colau, M.M., Nguyen, C., Palazzo, C., Srour, F., Paris, G., Vuillemin, V. et al. (2018) ‘Kinematic patterns in normal and degenerative shoulders. Part II: Review of 3-D scapular kinematic patterns in patients with shoulder pain, and clinical implications’, Annals of Physical and Rehabilitation Medicine. https://doi.org/10.1016/j.rehab.2017.09.002
[15] Spanhove, V., Calders, P., Berckmans, K., Palmans, T., Malfait, F., Cools, A. et al. (2022) ‘Electromyographic Muscle Activity and Three‐Dimensional Scapular Kinematics in Patients With Multidirectional Shoulder Instability: A Study in the Hypermobile Type of the Ehlers‐Danlos Syndrome and the Hypermobility Spectrum Disorders’, Arthritis Care & Research. https://doi.org/10.1002/acr.24525
[16] Higo, A., Palmer, S., Liaghat, B., Tallis, J., Silvester, L. and Pearce, G. (2024) ‘The Effectiveness of Conservative Interventions on Pain, Function, and Quality of Life in Adults with Hypermobile Ehlers-Danlos Syndrome/Hypermobility Spectrum Disorders and Shoulder Symptoms: A Systematic Review’, Archives of Rehabilitation Research and Clinical Translation. https://doi.org/10.1016/j.arrct.2024.100360
[17] Salamh, P.A., Hanney, W.J., Boles, T., Holmes, D., McMillan, A., Wagner, A. et al. (2023) ‘Is it Time to Normalize Scapular Dyskinesis? The Incidence of Scapular Dyskinesis in Those With and Without Symptoms: a Systematic Review of the Literature’, International Journal of Sports Physical Therapy. https://doi.org/10.26603/001c.74388
[18] Avila, M.A., Camargo, P.R., Ribeiro, I.L., Zamunér, A.R. and Salvini, T.F. (2014) ‘Three-dimensional scapular motion during arm elevation is altered in women with fibromyalgia’, Clinical Biomechanics. https://doi.org/10.1016/j.clinbiomech.2014.05.007


