- Hypermobile hip exercises we use, and why clamshells aren’t one of them - 17 October 2026
- Is Fibromyalgia a Disability in the UK, and Can You Claim PIP? - 14 October 2026
- Fibromyalgia and Central Sensitisation, What Is It in Plain English? - 8 October 2026
This article is part of our comprehensive guide to exercise and rehabilitation for hypermobility.
Your jaw clicks. It aches by the end of the day, usually worse on one side, and your teeth are touching whenever you happen to notice them. Sometimes the jaw catches on the way open and you have to shuffle it past something, and once or twice it’s gone somewhere it had no business going and took a frightening few seconds (or minutes) to get back in place.
The name for all of it, if anybody ever gotten around to giving you one, is TMJD, or TMD, a temporomandibular disorder. It means something is going wrong at the jaw joint or in the muscles working it, and that is the whole of what it means. It’s a label for a region rather than an explanation of what’s happening in it, which is most of the reason the advice sheets that come with it are so thin.
What follows in this post is the mechanism first, and then the practical part, because a routine handed over without the reasoning behind it, is generally how people end up doing the wrong exercises, very diligently, for months.
Is the jaw part hypermobility, or is that a coincidence?
If you’ve got hEDS, the jaw is part of it, and that’s about as consistent a finding as this field ever produces. If you’re hypermobile without a syndrome attached to it, the picture is a bit messier, and it splits according to which kind of jaw trouble you’ve actually got.
One phrase first, because it runs through every number you will find below. Inside each jaw joint there’s a small pad of tissue, and when that pad sits further forward than it should and then slots back into place as the joint moves, it’s called disc displacement with reduction. Displacement, because the pad is out of position. Reduction, because it goes back in. The click you can hear is the moment of going back. Two clicks, one on the way open and a quieter one on the way closed, is reciprocal clicking (fantastic band name don’t you think?).
Across the general adult population, temporomandibular disorders as a whole sit at around 31%, and disc displacement with reduction at around 26% [1]. In a small group with the hypermobile type of Ehlers-Danlos syndrome, 92.9% had a temporomandibular disorder [2]. In a mixed group with inherited connective tissue disease and generalised hypermobility, 71.4% were symptomatic for one [3]. Surveys covering classical and hypermobile EDS found masticatory muscle pain in at least 84.9%, painful or restricted jaw movement in 49.2% and TMJ dislocation in 49.4% [4]. And when women with confirmed hEDS were asked by questionnaire, nearly all of them reported symptoms of a temporomandibular disorder [5].
Two more words worth owning, because clinicians use them as though everybody already has them. Myalgia is muscle pain. Arthralgia is joint pain. In a jaw they are separate problems sharing an address, and they don’t behave the same way. Set against healthy controls, myalgia, myofascial pain that refers elsewhere, arthralgia, headache attributed to the jaw, disc displacement disorders and degenerative joint disease all turned up more often in hEDS [6].
Step outside of the syndromes for a moment, into generalised hypermobility on its own, and it stops being clean and tidy. The studies disagree, and they disagree in a pattern rather than at random: the ones counting discs and clicks tend to find something, and the ones counting pain mostly don’t.
In a population sample, generalised hypermobility went with a higher risk of reciprocal clicking and a lower risk of limited opening, and with no association at all with either myalgia or arthralgia [7]. Registry scale data found that people with disc related TMD were 6.7 times more likely to have joint hypermobility syndrome than people without a disc disorder [8]. A large young adult study found no overall association with chronic painful TMD, while still finding one with clicking and with the combined myalgia plus arthralgia subtype [9]. And some smaller cross sectional work found no significant association between generalised hypermobility and the signs of TMD at all [10], or none with clicking specifically [11]. Pulled together, the association comes out inconclusive [12].
Some of that disagreement is measurement rather than biology though. Hypermobility of the jaw, hypertranslation and subluxation are not defined the same way from one study to the next, so papers that look like they contradict each other are sometimes counting different things [13]. Hypertranslation just means the jaw travelling further forward out of the socket than it’s actually supposed to. Subluxation is the episodes where it goes too far and sticks. Count the travel in one study and the sticking in the next, and you get two different answers to what looks like one question.
So, it depends which question you’re actually asking. If yours is “is my clicking, catching, occasionally dislocating jaw connected to the rest of it”, the evidence points at yes and it points there fairly consistently (which is not something I get to say a lot). If yours is “is my jaw ache caused by being hypermobile”, that one is solid in hEDS and genuinely split outside of it.
What makes the jaw joint different from every other joint you have
The jaw is the only joint you own that has to come out of its socket to work properly (but it stays within the joint system supported by ligaments). Almost everything strange about a hypermobile one starts here.
You’ve got two temporomandibular joints, one either side of your head, just in front of each ear. Put your fingers there and open your mouth and you can feel them go. They’re joined to each other by a single bone, the mandible, which is your whole lower jaw in one piece, and that means you can’t move one without moving the other. There’s no other pair of joints in your body that works like that. Your left knee doesn’t care what your right knee is doing. Your jaw joints have no choice.
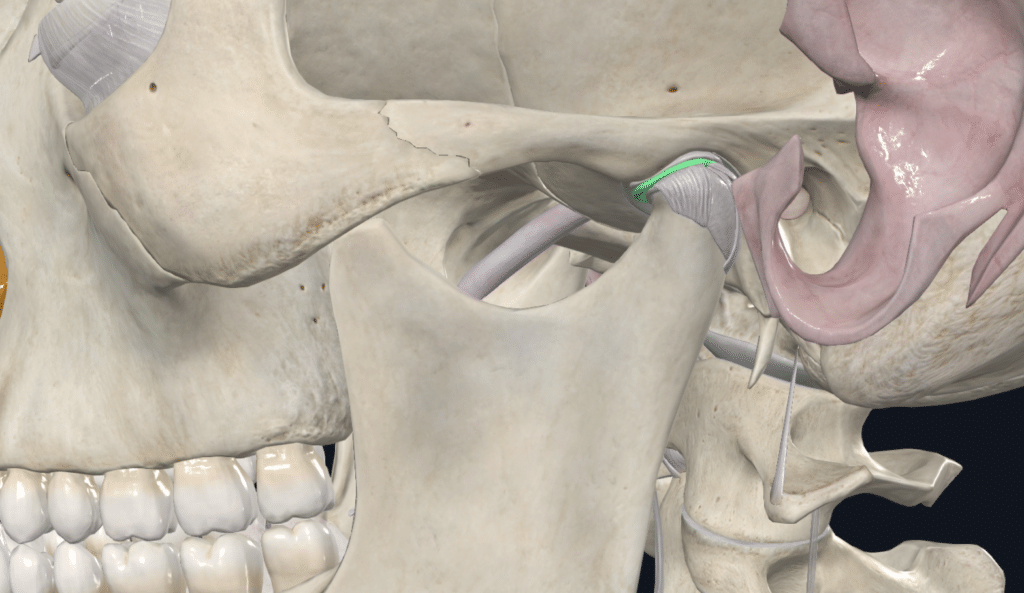
Each one has a disc in it, that small pad of fibrous tissue, sitting between the ball on the end of the jaw bone, called the condyle, and the socket in the skull above it. The disc isn’t free floating. It’s tethered, and part of what holds it where it belongs is a muscle, which is unusual, and which matters for what we have to say later.
And the movement itself is two movements. For the first part of opening, the condyle rotates in place, which is the hinge you’d expect. Then it stops hinging and starts sliding. It travels forwards and downwards, out of the socket and along a slope of bone in front of it called the articular eminence. On a wide open mouth it can arrive at the crest of that eminence or go past it, which is what the literature means by condylar translation [13]. The disc is supposed to come along for the ride, sitting between the condyle and the bone the whole way.
So, you’ve got a joint that leaves its socket as part of ordinary function, in a linked pair, with a mobile pad in the middle held partly by muscle, worked several thousand times a day by somebody who doesn’t think about it once. Now make the ligaments and the capsule a bit more giving than they ought to be. Nothing in the rest of this article is going to surprise you.
How would you know whether your jaw itself is hypermobile?
Your Beighton score won’t tell you, and that isn’t a technicality.
The Beighton is the fingers, thumbs, elbows, knees and reach to the floor check that probably got you the label in the first place, and it’s reliable at the job it was built for [15]. That job is generalised hypermobility. It doesn’t assess the temporomandibular joint at all, and using it on its own to conclude that the jaw is hypermobile is exactly what the reviews keep warning against [14]. A high Beighton tells you about your body. It tells you nothing specific about your face.
What does get used is how wide you can open. The thresholds treat mild jaw hypermobility as a maximum opening of 50 to 55 mm, moderate as 55 to 65 mm, and severe as more than 65 mm, with anything under 50 mm treated as a normal opening [13]. Adolescent work used an opening of 55 mm or more as a sign of jaw hypermobility and found it more often in hypermobile girls than in the rest [16]. If you want the number, it’s measured between the edges of your upper and lower front teeth, at the point where opening any further stops being comfortable. A ruler and a mirror will do it. The rougher version, the one you’ll meet in a dental chair, is whether your own index, middle and ring fingers stack into the gap.
Don’t read too much into the result, though, because the ruler is a blunt instrument here. The increases in opening that came with generalised hypermobility were often small enough not to matter clinically [7]. How far the condyle actually travels on imaging does not map reliably onto how wide the mouth opens in the chair [17]. A condyle sitting at or beyond the crest of the eminence can turn up in people who have no trouble with their jaw at all [13]. And imaging parameters on their own had limited predictive value for whether somebody open locks or subluxes [18].
Which gives you the more useful test, and it’s a history rather than a measurement. In the studios, the question that sorts this out is not how wide the jaw goes. It’s whether it has ever stuck open, and what you had to do to get it closed again. In the diagnostic criteria, a subluxation is an open lock episode that either sorts itself out or needs a specific manoeuvre to reduce it, while a luxation or dislocation is one that needs professional help [13]. Those are two different things wearing similar words, and which of them you’ve had tells you more than any figure off a ruler.
If your jaw has not locked open, and it’s simply wide and a bit noisy, It’s a different situation from the one below.

Why a loose jaw ends up feeling tight
People describe this one the same way over and over: loose and tight at once. It reads like a contradiction and it isn’t one.
A joint gets held in place two ways. There’s the passive side, the ligaments and the capsule, tissue that does its job without anybody asking, and there’s the active side, which is muscle. When the passive side gives more than it ought to, the active side picks the work up. Muscle is perfectly capable of it. It’s a much more expensive way of holding a joint still, though, because a muscle has to be switched on to do anything at all, and it tires, and it gets sore, and unlike a ligament it can tell you about it. A ligament holds you for free. A muscle sends a bill.
That’s the tightness people in this community are describing. Not shortened tissue. A jaw being held rather than supported. The resting position of the lower jaw drifts from hanging quietly to gently gripped, and then it stays there through a work call, a commute and an argument with a form, and by nine at night the side you favour is aching from the ear down.
Now, for something most people don’t know: your teeth aren’t meant to be touching. At rest, the back teeth should be slightly apart, your lips closed. Teeth come together to eat and to swallow, and then they part again. When masticatory muscle activity was measured with electrodes in people with hypermobile jaws, it came out reduced during clenching and during chewing, and chewing efficiency was worse in the more severe hypermobility [19]. That’s the opposite direction from the one you’d predict from a jaw that’s permanently gripped.
Electrodes on the cheek record a muscle doing a task, in a chair, for a few seconds: bite down hard, chew this. What they’re built to capture is effort on demand. A low grade hold that runs all day and causes an ache at bedtime is a different thing on a different timescale.
What isn’t in dispute is the pain. Pain on pressing the masseter and the temporalis, orofacial pain, pain on moving the jaw and a myalgia diagnosis were all more common in hEDS than in controls [6]. Those two are the muscles you can find yourself. The masseter is the slab of meat at the angle of your jaw that bulges when you bite down. The temporalis is the fan above and in front of your ear that moves under your fingers when you chew. If you’ve ever pressed either of them and found a spot that made you swear a little, that’s the muscle.
Bruxism, the clenching and grinding that nobody in this community actually calls bruxism, gets treated as the villain here, and the confidence around that outruns the evidence for it time and time again. It’s described as a likely aggravating factor in a hypermobile jaws, something that piles load onto a joint already short of restraint, rather than as something hypermobility has been shown to cause [20]. In women with hEDS or HSD who had TMD symptoms, reporting bruxism went with worse oral health related quality of life [21]. And step outside hypermobility altogether and the argument that sustained heavy bruxing is the general explanation for painful myofascial TMD does’nt hold up well [22][23].
So, the clenching is worth addressing and it isn’t the whole story, and treating it as the whole story is how people end up working very hard on one input while the rest carries on regardless. The cheapest thing on this page is the resting position above. Teeth apart, tongue up, lips together, checked a few times a day until it stops needing checking. It’s the thing I say to people most often about jaws and it costs nothing.
Clicking, catching and getting stuck
Three different events, and they worry people for three different reasons.
The click is about the disc. When the disc sits further forward than it should, the condyle has to get back underneath it on the way open, and the moment it does, there’s a click. On the way closed the condyle comes off the front edge of the disc again, and there’s a second, usually quieter one. That’s the reciprocal clicking from earlier, and it’s the audible version of disc displacement with reduction.
It’s also the pattern hypermobility lines up with most reliably. In the population data, generalised hypermobility went with a higher risk of reciprocal clicking [7]. In registry data, people with a disc related TMD were 6.7 times more likely to have joint hypermobility syndrome [8]. In a hypermobile adult group, disc dislocation with reduction was present in 85.7% and recurrent dislocations turned up more often than in non hypermobile people with TMD [3].
Crepitation is the other noise. A click is one event, sharp, at a particular point in the movement. Crepitation is gritty, and it runs through the movement rather than punctuating it. In hEDS, disc displacement disorders, locking, crepitation and degenerative joint disease were all more common than in healthy controls [6].
Catching is the click with more friction. The disc isn’t sliding back into place cleanly, so instead of a crisp noise you get a snag, and you find yourself moving the jaw sideways or forwards to get past it. People work out their own route through it, usually without being taught.
Locking is the one that frightens people the most, and it comes in two versions that get confused constantly. A closed lock is a jaw that won’t open far, because the disc has stopped letting the condyle past it. An open lock is a jaw that won’t close, because the condyle has gone forward past the eminence and can’t get back. The second is the hypermobility flavoured version, and it’s the one people mean when they say their jaw has gone out.
Surveys across classical and hypermobile EDS reported TMJ dislocation in 49.4% [4]. And groups of people presenting with recurrent TMJ dislocation turn out to be enriched for generalised hypermobility [24].
A condyle that travels past the eminence can turn up in people with no symptoms at all [13], and imaging on its own was a poor predictor of who open locks and who does not [18]. A jaw that goes a long way isn’t the problem. The problem, where there is one, is a jaw that goes a long way and then doesn’t come back in a controlled way.
What to do when it goes out
Before the practical part, this is clinical pattern rather than literature. Take it as what we do rather than as evidence.
Don’t force it shut. The reflex when a jaw locks open is to push upwards hard, and pushing up makes the muscles around it grip harder, which is the thing actually stopping it going back. The condyle is caught in front of a slope of bone. It has to travel down first and then back, not straight up.
So: support the weight of the jaw with your hand underneath it, get your breathing slow, and give the muscles a minute before you try anything. Warmth over the joint and over the muscle in front of your ear helps them let go, and a wheat bag against the side of your face is as good a tool as anything sold for the job. Then try small movements rather than one big effort, side to side first, and let the jaw find its own way rather than driving it.
If it goes back, expect it to be sore for a few days and expect to be on soft food. Soreness after a joint has been out and gone back in comes mostly from the muscles that spent time gripping, and it does settles.
If it doesn’t go back, stop. A jaw that needs somebody else to sort it is, by the definition used in the diagnostic criteria, a dislocation rather than a subluxation [13]. That’s an A and E job (or ER, for those reading in certain break away British territories, wot wot), and it’s worth knowing what they’ll do so it holds no surprises: the same principle as above, performed by somebody with both thumbs free and a better angle, pressing down on your back teeth and guiding the jaw backwards while the muscles are persuaded to let go. It’s short, undignified and thoroughly routine, and nobody there thinks less of you for turning up with it.
The other thing worth doing is noticing what set it off. Yawning is the classic. So is a long dental appointment with your mouth propped open, an unusually big sandwich, singing, laughing, or a dentist who hasn’t been told about the hypermobility. Capping the yawn with a fist under the chin, asking for breaks during dental work, and saying the word hypermobile out loud before anybody reaches for the dental tools: all cheap, all boring, all habit rather than treatment. The teeth and the dental appointment side of this has a post of its own, so it isn’t re-argued here.
Why the standard jaw exercise sheet was written for somebody else
Most of what’s printed on a TMJ exercise sheet was designed for a jaw that won’t open far enough. Yours opens too easily. So the stretches at the top of the sheet aim at a problem you don’t have, and in a couple of cases at the opposite of the problem you do have.
That isn’t an argument against exercise, because the exercise evidence in TMD generally is reasonable. Pooling 153 randomised trials and 8,713 people, the options that came out best for pain were cognitive behavioural therapy with biofeedback or relaxation, jaw mobilisation done by a therapist, and trigger point therapy [25]. Supervised postural exercise, and supervised jaw exercise with stretching, were also supported, and jaw exercise and stretching probably improves physical functioning [25]. The certainty around adverse events in all of it was low or very low [25].
Underneath that headline, the individual findings go the same way with smaller effects. Exercise therapy reduced pain and improved both active and passive mouth opening, with stronger effects when it was added to a splint [26]. An earlier review judged the overall evidence low quality and found no clear superiority for exercise over other conservative treatments, while noting that manual therapy combined with jaw or neck exercise looked promising [27]. Of the various things called exercise, coordination work showed the clearest benefits in a focused review of the pain related TMD trials [28].
The trials that went after clicking specifically are worth pulling out, because clicking is what brings people to a page like this one. Supervised exercise for symptomatic disc displacement with reduction improved the joint sounds and brought pain and psychosocial burden down with them [29], and adding jaw exercises to counselling improved how much the clicking bothered people [30]. Mandibular exercises improved pain free mouth opening more than splint based conservative care did [31]. Neck motor control training can improve pain, function and quality of life in myofascial or mixed TMD [32], and so can cranio-mandibular stabilisation exercise [33].
Then the part that matters for you. Almost none of that was done in people with hEDS or generalised hypermobility [25][26][34]. The one piece of work aimed straight at the overlap found that TMD focused physiotherapy reduced myofascial pain and improved how well the jaw coordinated its movements in people who also had joint hypermobility syndrome [35], and that was a snapshot rather than a trial. Proprioception, while we’re here, is your sense of where a joint is without looking at it, and it’s the sense a loose joint reports badly. Reviews of exercise and rehabilitation in EDS outside the jaw suggest that exercise and proprioception focused work can help pain and function generally [37][38]. In jaw hypermobility groups specifically, non surgical protocols can bring pain, joint sounds and maximum opening down over follow up, on uncontrolled evidence and not in a hypermobility syndrome [39].
So we’re borrowing, and we should say so. The sensible reading of all of it is the one the broader guidance already gives: start conservative, start reversible, use more than one thing at once, and escalate only if that fails [36].
What we’d change for a hypermobile jaw
Control before range. The aim isn’t a wider opening. You’ve got plenty of opening. The aim is a jaw that opens the same way twice, tracks straight, and doesn’t wander off to one side halfway down. That’s coordination work, which is the category that showed the clearest benefits in the pain related TMD trials anyway [28].
Small, slow and often. A hypermobile joint doesn’t need a big dose. It needs a clear, repeatable input at a range where nothing snags. Working into the click, through the catch, or out to your maximum opening isn’t making the joint stronger. It’s teaching the muscles to brace harder.
The neck comes with it. The head sits on the neck and the jaw hangs off the head, and neck motor control training can improve pain, function and quality of life in myofascial or mixed TMD [32]. If your neck is doing its own version of this, treating the jaw on its own is working on half the problem.
In practice that’s three unremarkable things, done in front of a mirror, with a fingertip resting lightly over each joint so you can feel whether the two sides are going together.
The resting position, which you already have. Teeth apart, tongue up behind the front teeth, lips closed, jaw heavy. Not held there. Allowed there. This one belongs at traffic lights and in meetings rather than in a session.
Tracking. Tongue up on the roof of your mouth, then open slowly, only as far as the tongue will stay put, and close just as slowly. The tongue is there to keep you short of the range where things snag, which is the whole trick of it. Watch the midline of your chin in the mirror and keep it running straight down. If it drifts off to one side, that drift is the thing you’re training, and the answer is slower rather than further.
Glide. Jaw relaxed, teeth apart. Slide the lower jaw forward a short way and back, then to one side and back, then the other. Small, slow, and nowhere near your end range.
None of it should hurt and none of it should be tiring. Little and often is the entire idea: a short go in the morning and another in the evening will do more than one long session, and stopping while it still feels easy is the point rather than a cop out. If your jaw is sore the next day, you did too much. That’s an easy mistake to make and it’s not a disaster, it means going smaller.
The lateral pterygoid, and the exercise that goes with it
Of all the muscles round the jaw, this is the one that gets named, and there’s a reason for it.
The lateral pterygoid sits deep, behind and above the angle of your jaw, running roughly horizontally, and you can’t get a finger on it from the outside. It has two heads. The lower one pulls the condyle forwards, which is what happens when you stick your chin out or slide your jaw sideways, and it’s what takes over during the sliding half of opening. The upper one attaches into the joint capsule and into the disc itself. That’s the unusual bit from earlier: the disc has a muscle attached to it, and this is that muscle.
Which is why it gets targeted. If the disc is sitting too far forward and clicking back into place, the muscle with a direct hold on the disc is an obvious place to look. Jaw hypermobility in EDS is described as promoting subluxation and dislocation and, in doing so, adding strain to the disc, the ligaments and the chewing muscles [20], so the lateral pterygoid sits in the middle of that traffic.
Worth being careful with it, though. Coordination exercise as a category came out best of the exercise options in pain related TMD [28], and supervised exercise in symptomatic disc displacement with reduction improved the joint sounds along with the pain [29]. The pterygoid work sits inside that category. It isn’t a special case with rules of its own.
The work itself is the glide above, done with attention. Sliding forward and sliding sideways, small and slow, jaw relaxed, teeth apart, tongue up, fingertips on the joints. In front of a mirror, because the whole point is the tracking, and you can’t feel your own deviation nearly as well as you can see it. Stop short of the click rather than pushing through it, and stop a long way short of your maximum. If it’s sore afterwards you’ve done too much of it, which with this muscle is easily done.
The short version
Best return: coordination and control work for the jaw, done small and often, plus the resting position. Coordination came out best among the exercise options for pain related TMD [28], and supervised exercise improved joint sounds in disc displacement with reduction [29].
Worth doing alongside it: the neck. Neck motor control training can improve pain, function and quality of life in myofascial or mixed TMD [32].
Worth doing and boring: capping yawns, warning the dentist, taking breaks during dental work, noticing what precedes the bad days. All of it free, and all of it habit rather than treatment.
Worth asking about rather than buying: anything aimed at forcing more opening. You have the opening. Jaw exercise and stretching probably improves physical functioning [25], and almost none of that work was done in hypermobile people [25][26][34].
Ask for help with, don’t manage alone: a jaw that has locked open and won’t reduce. That’s a dislocation by definition, and it’s a hospital rather than a home job [13].
Untested in hypermobility: nearly all of the treatment evidence above [25][26][34].
If you take one thing away, make it this. A jaw that feels tight isn’t a jaw that needs stretching. It’s a jaw doing a holding job it wasn’t built for, because the tissue that should be doing it has gone quiet. Change what the muscles are being asked to do and the tightness has a reason to stop. Stretch it and you’re pulling on the only thing currently keeping the joint where it belongs.
Adam

References
[1] Valesan, L.F., Da-Cas, C.D., Réus, J.C., Denardin, A.C.S., Garanhani, R.R., Bonotto, D. et al. (2021) ‘Prevalence of temporomandibular joint disorders: a systematic review and meta-analysis’, Clinical Oral Investigations. https://doi.org/10.1007/s00784-020-03710-w
[2] Diep, D., Fau, V., Wdowik, S., Bienvenu, B., Bénateau, H. and Veyssière, A. (2016) ‘Dysfonction de l’appareil manducateur et syndrome d’Ehlers-Danlos de type hypermobile : étude cas-témoin’, Revue de Stomatologie, de Chirurgie Maxillo-faciale et de Chirurgie Orale. https://doi.org/10.1016/j.revsto.2016.07.009
[3] De Coster, P., Van Den Berghe, L. I. and Martens, L. (2005) ‘Generalized joint hypermobility and temporomandibular disorders: inherited connective tissue disease as a model with maximum expression’, Journal of Orofacial Pain. PMID: 15779539
Read More[4] Willich, L., Bohner, L., Köppe, J., Jackowski, J., Hanisch, M. and Oelerich, O. (2023) ‘Prevalence and quality of temporomandibular disorders, chronic pain and psychological distress in patients with classical and hypermobile Ehlers-Danlos syndrome: an exploratory study’, Orphanet Journal of Rare Diseases. https://doi.org/10.1186/s13023-023-02877-1
[5] Yekkalam, N., Novo, M., Tyrberg, M.J. and Sipilä, K. (2024) ‘Risk factors associated with symptoms of temporomandibular disorders among women with hypermobile Ehlers–Danlos syndrome: Questionnaire‐based study in Finland and Sweden’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.13706
[6] Bech, K., Fogh, F.M., Lauridsen, E.F. and Sonnesen, L. (2022) ‘Temporomandibular disorders, bite force and osseous changes of the temporomandibular joints in patients with hypermobile Ehlers‐Danlos syndrome compared to a healthy control group’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.13348
[7] Hirsch, C., John, M.T. and Stang, A. (2008) ‘Association between generalized joint hypermobility and signs and diagnoses of temporomandibular disorders’, European Journal of Oral Sciences. https://doi.org/10.1111/j.1600-0722.2008.00581.x
[8] Chang, T.H., Yuh, D.Y., Wu, Y.T., Cheng, W.C., Lin, F.G., Shieh, Y.S. et al. (2015) ‘The association between temporomandibular disorders and joint hypermobility syndrome: a nationwide population-based study’, Clinical Oral Investigations. https://doi.org/10.1007/s00784-015-1422-7
[9] Barbosa, C., Gavinha, S., Soares, T., Reis, T. and Manso, C. (2024) ‘Is Generalized Joint Hypermobility Associated with Chronic Painful Temporomandibular Disorders in Young Adults? A Cross-Sectional Study’, Journal of Clinical Medicine. https://doi.org/10.3390/jcm14010044
[10] Chiodelli, L., Pacheco, A.D.B., Missau, T.S., Silva, A.M.T.D. and Corrêa, E.C.R. (2016) ‘Influência da hipermobilidade articular generalizada sobre a articulação temporomandibular e a oclusão dentária: estudo transversal’, CoDAS. https://doi.org/10.1590/2317-1782/20162014082
[11] Sanguinetti, M., Minvielle, M. and Riva, R. (2021) ‘Asociación entre Hiperlaxitud Articular Generalizada y Chasquidos de la Articulación Témporo Mandibular’, Odontoestomatología. doi: 10.22592/ode2021n37a3
[12] Dijkstra, P.U., Kropmans, T.J.B. and Stegenga, B. (2002) ‘The Association between Generalized Joint Hypermobility and Temporomandibular Joint Disorders: A Systematic Review’, Journal of Dental Research. https://doi.org/10.1177/0810158
[13] BRAGA, S.P., CUNHA, C.O., MICHELOTTI, A., BONJARDIM, L.R. and CONTI, P.C.R. (2025) ‘Association between generalized joint hypermobility, temporomandibular joint hypertranslation and temporomandibular disorders: a scoping review’, Journal of Applied Oral Science. https://doi.org/10.1590/1678-7757-2024-0302
[14] Malek, S., Reinhold, E.J. and Pearce, G.S. (2021) ‘The Beighton Score as a measure of generalised joint hypermobility’, Rheumatology International. https://doi.org/10.1007/s00296-021-04832-4
[15] Bockhorn, L.N., Vera, A.M., Dong, D., Delgado, D.A., Varner, K.E. and Harris, J.D. (2021) ‘Interrater and Intrarater Reliability of the Beighton Score: A Systematic Review’, Orthopaedic Journal of Sports Medicine. https://doi.org/10.1177/2325967120968099
[16] Graf, C., Schierz, O., Steinke, H., Körner, A., Kiess, W., Kratzsch, J. et al. (2019) ‘Sex hormones in association with general joint laxity and hypermobility in the temporomandibular joint in adolescents—results of the epidemiologic LIFE child study’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.12834
[17] Taylor, D.J., Gould, D.E., Arman, D.S. and Mallya, D.S. (2025) ‘Does open-mouth temporomandibular joint computed tomographic imaging provide added value in the diagnosis of temporomandibular disorders?’, Oral Surgery, Oral Medicine, Oral Pathology and Oral Radiology. https://doi.org/10.1016/j.oooo.2024.11.031
[18] Braga, S.P., Salbego, R.S., Carneiro, C.A., Berden, M.E.S., Cunha, C.O., Bonjardim, L.R. et al. (2026) ‘Predictive Value of TMJ Tomographic Parameters for Hypermobility‐Related Outcomes and Mouth Opening Capacity’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.70194
[19] Davoudi, A., Haghighat, A., Rybalov, O., Shadmehr, E. and Hatami, A. (2015) ‘Investigating activity of masticatory muscles in patients with hypermobile temporomandibular joints by using EMG’, Journal of Clinical and Experimental Dentistry. https://doi.org/10.4317/jced.52125
[20] Mitakides, J. and Tinkle, B.T. (2017) ‘Oral and mandibular manifestations in the Ehlers–Danlos syndromes’, American Journal of Medical Genetics Part C: Seminars in Medical Genetics. https://doi.org/10.1002/ajmg.c.31541
[21] Yekkalam, N., Sipilä, K., Novo, M., Reissmann, D., Hanisch, M. and Oelerich, O. (2024) ‘Oral health–related quality of life among women with temporomandibular disorders and hypermobile Ehlers-Danlos syndrome or hypermobility spectrum disorder’, The Journal of the American Dental Association. https://doi.org/10.1016/j.adaj.2024.08.013
[22] Santiago, V. and Raphael, K. (2019) ‘Absence of joint pain identifies high levels of sleep masticatory muscle activity in myofascial temporomandibular disorder’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.12853
[23] Nickel, J.C., Gonzalez, Y.M., Gallo, L.M. and Iwasaki, L.R. (2024) ‘The challenge of ecological validity in temporomandibular disorders research’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.13707
[24] Cohen, A., Sela, M.C., Ran, L.Z., Rushinek, H., Talisman, S. and Casap, N. (2023) ‘Increased Prevalence of Generalized Joint Hypermobility Observed in Patients With Recurrent Temporomandibular Joint Dislocation’, Journal of Oral and Maxillofacial Surgery. https://doi.org/10.1016/j.joms.2023.04.006
[25] Yao, L., Sadeghirad, B., Li, M., Li, J., Wang, Q., Crandon, H.N. et al. (2023) ‘Management of chronic pain secondary to temporomandibular disorders: a systematic review and network meta-analysis of randomised trials’, BMJ. https://doi.org/10.1136/bmj-2023-076226
[26] Idáñez-Robles, A.M., Obrero-Gaitán, E., Lomas-Vega, R., Osuna-Pérez, M.C., Cortés-Pérez, I. and Zagalaz-Anula, N. (2022) ‘Exercise therapy improves pain and mouth opening in temporomandibular disorders: A systematic review with meta-analysis’, Clinical Rehabilitation. https://doi.org/10.1177/02692155221133523
[27] Armijo-Olivo, S., Pitance, L., Singh, V., Neto, F., Thie, N. and Michelotti, A. (2016) ‘Effectiveness of Manual Therapy and Therapeutic Exercise for Temporomandibular Disorders: Systematic Review and Meta-Analysis’, Physical Therapy. https://doi.org/10.2522/ptj.20140548
[28] Shimada, A., Ogawa, T., Sammour, S.R., Narihara, T., Kinomura, S., Koide, R. et al. (2023) ‘Effectiveness of exercise therapy on pain relief and jaw mobility in patients with pain-related temporomandibular disorders: a systematic review’, Frontiers in Oral Health. https://doi.org/10.3389/froh.2023.1170966
[29] Wänman, A. and Marklund, S. (2019) ‘Treatment outcome of supervised exercise, home exercise and bite splint therapy, respectively, in patients with symptomatic disc displacement with reduction: A randomised clinical trial’, Journal of Oral Rehabilitation. https://doi.org/10.1111/joor.12888
[30] Simões, C.A.S.C., da Silva, M.A.M., Magesty, R.A., Falci, S.G.M., Douglas-de-Oliveira, D.W., Gonçalves, P.F. et al. (2023) ‘Counselling treatment versus counselling associated with jaw exercises in patients with disc displacement with reduction—a single-blinded, randomized, controlled clinical trial’, BMC Oral Health. https://doi.org/10.1186/s12903-023-03096-7
[31] De Negreiros, W. A., Regis, R., De Mello Fiallos, A. C., Rocha, J. E. T., Nogueira, I. A. D., De Barros Silva, P. G. and Peixoto, R. F. (2025) ‘Effect of mandibular exercises in the control of signs and symptoms of temporomandibular disorders: a randomized controlled clinical trial’, Quintessence International. doi: 10.3290/j.qi.b5984433
[32] De Oliveira-Souza, A. L. S., De Oliveira, D. A. and Armijo-Olivo, S. (2024) ‘Effectiveness of an 8-week neck exercise training on pain, jaw function, and oral health-related quality of life in women with chronic temporomandibular disorders: a randomized controlled trial’, Journal of Oral & Facial Pain and Headache. doi: 10.22514/jofph.2024.005
[33] Patra, R.C. and Yashudas, A. (2025) ‘Evaluating the efficacy of cranio-mandibular stabilization exercises on pain, jaw mobility, mouth function, and oral health-related quality of life in patients with temporomandibular disorder management: A randomized controlled trial’, Journal of Back and Musculoskeletal Rehabilitation. https://doi.org/10.1177/10538127251361631
[34] Engelbert, R.H.H., Juul‐Kristensen, B., Pacey, V., de Wandele, I., Smeenk, S., Woinarosky, N. et al. (2017) ‘The evidence‐based rationale for physical therapy treatment of children, adolescents, and adults diagnosed with joint hypermobility syndrome/hypermobile Ehlers Danlos syndrome’, American Journal of Medical Genetics Part C: Seminars in Medical Genetics. https://doi.org/10.1002/ajmg.c.31545
[35] Kulesa-Mrowiecka, M., Piech, J. and Gaździk, T.S. (2021) ‘The Effectiveness of Physical Therapy in Patients with Generalized Joint Hypermobility and Concurrent Temporomandibular Disorders—A Cross-Sectional Study’, Journal of Clinical Medicine. https://doi.org/10.3390/jcm10173808
[36] Tran, C., Ghahreman, K., Huppa, C. and Gallagher, J.E. (2022) ‘Management of temporomandibular disorders: a rapid review of systematic reviews and guidelines’, International Journal of Oral and Maxillofacial Surgery. https://doi.org/10.1016/j.ijom.2021.11.009
[37] Buryk-Iggers, S., Mittal, N., Santa Mina, D., Adams, S.C., Englesakis, M., Rachinsky, M. et al. (2022) ‘Exercise and Rehabilitation in People With Ehlers-Danlos Syndrome: A Systematic Review’, Archives of Rehabilitation Research and Clinical Translation. https://doi.org/10.1016/j.arrct.2022.100189
[38] Reychler, G., De Backer, M., Piraux, E., Poncin, W. and Caty, G. (2021) ‘Physical therapy treatment of hypermobile Ehlers–Danlos syndrome: A systematic review’, American Journal of Medical Genetics Part A. https://doi.org/10.1002/ajmg.a.62393
[39] Hegab, A.F., Shuman, M., Al Hameed, H.A. and Karam, K. (2026) ‘Classification of temporomandibular joint hypermobility based on lateral TMJ, and magnetic resonance imaging contributing to a nonsurgical treatment protocol’, Scientific Reports. https://doi.org/10.1038/s41598-026-36461-x